We need you! Join our contributor community and become a WikEM editor through our open and transparent promotion process.
Pediatric head trauma
From WikEM
(Redirected from Pediatric Head Trauma)
Contents
Background
- TBI in the pediatric population is rare, occuring in 0.9% of the 42,412 PECARN population
- PECARN rules have become standard of care
- In patients <2 yrs the aid is 100% sensitive with NPV of 100%
- In patient >2 yrs the aid is 96.8% sensitive with NPV of 99.95% (with validation studies showing sensitivity of 100% for TBI and injury requiring neurosurgery
Clinical Features
- Persistence of headache, confusion, and amnesia suggests concussion
- Nonfrontal scalp hematoma in <2yo is associated with increased risk of Skull Fracture, ICH
- Clinical symptoms (headache, vomiting, behavior change) do not correlate well with ICH
Differential Diagnosis
Intracranial Hemorrhage
- Intra-axial
- Hemorrhagic stroke (Spontaneous intracerebral hemorrhage)
- Traumatic intracerebral hemorrhage
- Extra-axial
- Epidural hemorrhage
- Subdural hemorrhage
- Subarachnoid hemorrhage (aneurysmal intracranial hemorrhage)
Concussion
Maxillofacial Trauma
- Le Fort fractures
- Skull fracture (peds)
- Auricular hematoma
- Nasal fracture
- Zygomatic arch fracture
- Zygomaticomaxillary (tripod) fracture
- Dental trauma
- Mandible fracture
Orbital trauma
Acute
- Ruptured Globe^
- Corneal Abrasion
- Ocular foreign body
- Conjunctival laceration
- Caustic Keratoconjunctivitis^^
- Subconjunctival hemorrhage
- Traumatic iritis
- Traumatic hyphema
- Retinal detachment
- Retrobulbar hemorrhage/hematoma
- Traumatic mydriasis
- Orbital fracture
- Frontal sinus fracture
- Naso-ethmoid fracture
- Inferior orbial wall fracture
- Medial orbital wall fracture
Subacute/Delayed
Evaluation
Pediatric GCS[1][2]
| Eye Opening | Verbal | Motor |
| 6: Normal spontaneous movement | ||
| 5: Smiles, coos, babbles | 5: Withdraws to touch | |
| 4: Opens eyes spontaneously | 4: Irritable, crying (but consolable) | 4: Withdraws to pain |
| 3: Opens eyes to speech only | 3:Inconsolable crying or crying only in response to pain | 3: Abnormal flexion to pain (Decorticate response) |
| 2: Opens eyes to pain only | 2: Moans in response to pain | 2: Abnormal extension to pain (Decerebrate response) |
| 1: Does not open eyes | 1: No response | 1: No response |
Note:
- For Motor score 4, pain is defined flat, fingernail pressure (often performed with the barrel of a pencil).
- For Motor scores 2 and 3, pain is defined by pressing hard on the supraorbital notch. If this unsuccessful, sternal pressure may also be attempted.
Adult GCS
| Eye Opening | Verbal | Motor |
| 6: Obeys commands | ||
| 5: Oriented | 5: Localizes to pain | |
| 4: Spontaneously opens | 4: Confused speech | 4: Withdraws from pain (normal flexion) |
| 3: Opens to command | 3:Inappropriate words | 3: Decorticate posturing (abnormal flexion) |
| 2: Opens to pain | 2: Incomprehensible sounds | 2: Decerebrate posturing (extension) |
| 1: Does not open | 1: No response | 1: No response |
- 14-15: Mild
- 9-13: Moderate
- 3-8: Severe
Work-Up
Rules below are with the application of PECARN [3]
Management
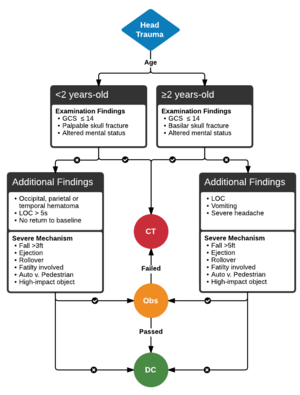
<2 years old
Any 1 of the following?
- GCS ≤14
- Altered Mental Status
- Palpable Skull Fracture
Then obtain a Non-Con Brain CT (4.4% risk of cTBI)
1 or more of the following?
- Non-frontal scalp hematoma
- LOC ≥ 5 seconds
- Severe injury mechanism
- pedestrian or bicyclist without helmet struck by motorized vehicle
- fall >1m or 3ft
- head struck by high-impact object
- Abnormal activity per parents
Then consider a Non-Con Brain CT or Observation (0.9% risk of cTBI)
≥2 years old - 18 years
Any 1 of the following?
- GCS ≤14
- Altered Mental Status
- Signs of a basilar skull fracture
Then obtain a Non-Con Brain CT (4.3% risk of cTBI)
1 or more of the following?
- History of vomiting^
- LOC
- Severe injury mechanism
- Pedestrian or bicyclist without helmet struck by motorized vehicle
- Fall >2m or 5ft
- Head struck by high-impact object
- Severe headache
Then consider a Non-Con Brain CT or Observation (0.9% risk of cTBI)
^Consider observation in place of imaging in children with isolated vomiting (no other indication) as the sole risk factor (0.2% risk of cTBI)[4]
Disposition
- Discharge if:
- Asymptomatic after 2-4hr obs (not vomiting, nl neuro exam, nl mental status)
- Head CT normal (delayed deterioration after normal CT is near zero)
- Consider discharge if:
- Nondisplaced fracture with out intracranial injury (in consultation with neurosx)
See Also
General/Adult
Pediatric
External Links
References
- ↑ Holmes JF, Palchak MJ, MacFarlane T, et al. Performance of the pediatric glasgow coma scale in children with blunt head trauma. Acad Emerg Med. 2005 Sep;12(9):814-9.
- ↑ James HE. Neurologic evaluation and support in the child with an acute brain insult. Pediatr Ann. 1986 Jan;15(1):16-22.
- ↑ PECARN Rule Kupperman N, Holmes JF, Dayan PS, et al: Identification of children at very low risk of clinically-important brain injuries after head trauma: a prospective cohort study. Lancet 374(9696): 1160, 2009
- ↑ Dayan PS, et al. "Association of Traumatic Brain Injuries with Vomiting in Children with Blunt Head Trauma. June 2014. Annals of EM. 63(6):657-665

